Saturday, October 24, 2026 · Dogs
Snakebite in Dogs: Antivenom, Supportive Care and New Research
Noted by Castillo, Therese · 416 reads
Antivenom and close monitoring remain central to dog snakebite care. Learn what signs can signal severe envenomation and what research is testing.
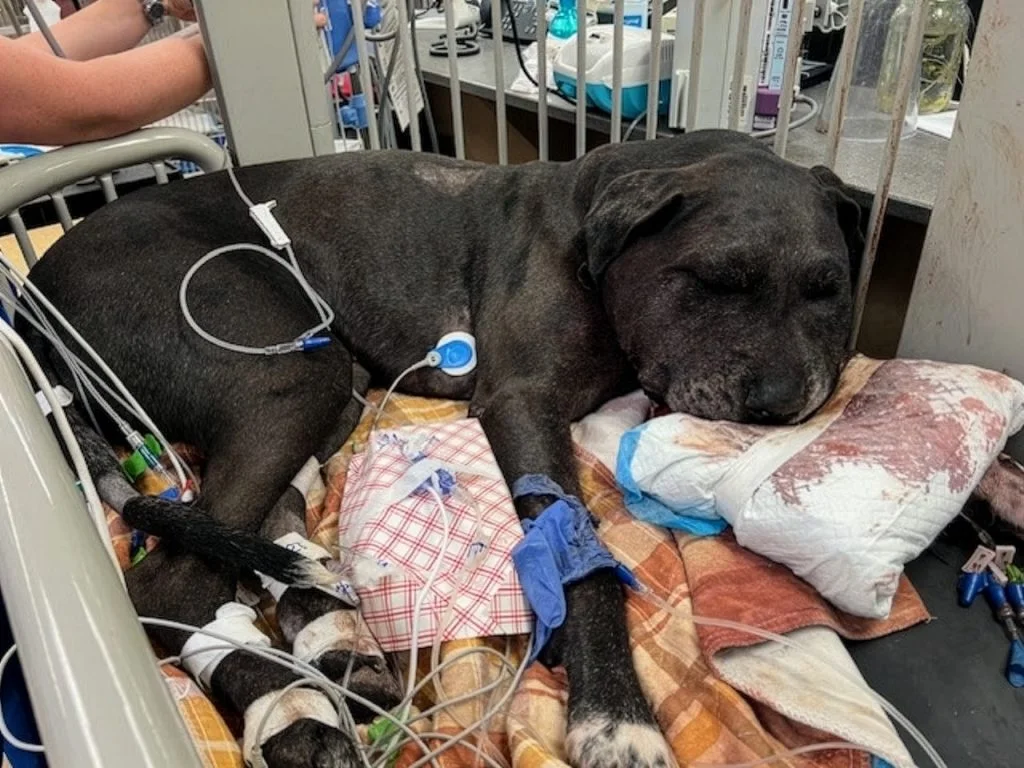
For dogs with significant snake envenomation, prompt assessment and antivenom when indicated remain central to care. The challenge is that a dramatic bite wound doesn’t always signal the most dangerous effects: some rattlesnake and coral snake bites can cause severe systemic or neurologic illness while local signs are subtle. Close monitoring matters because blood abnormalities and other complications may emerge hours after a dog first arrives.
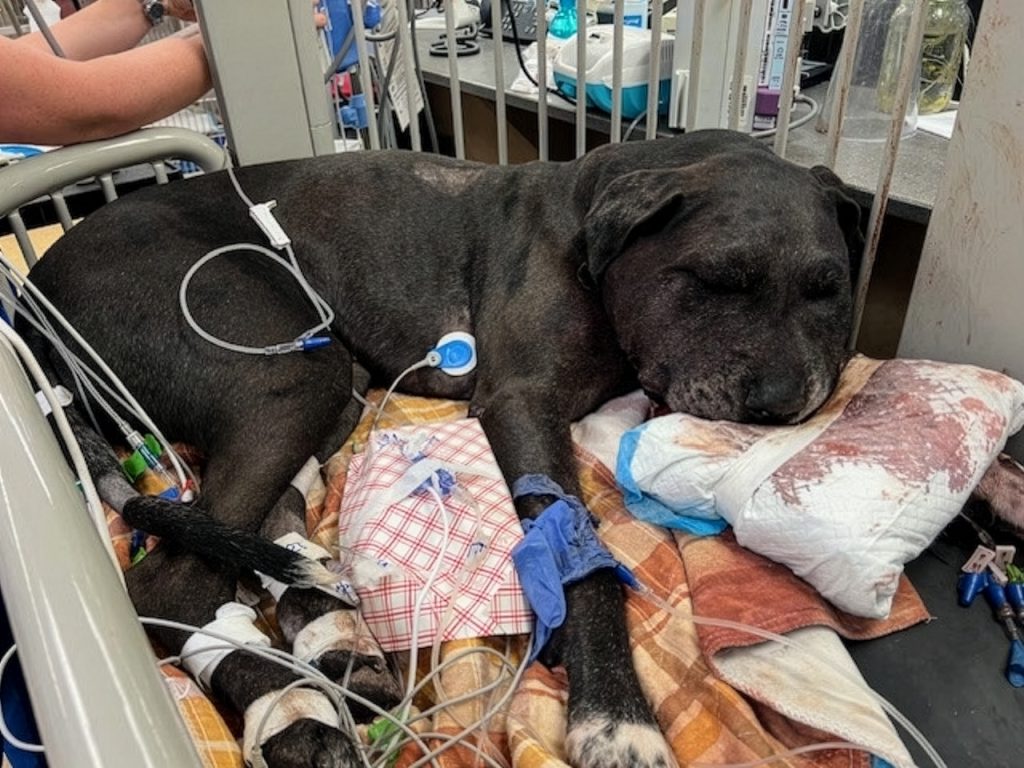
Venom effects can vary
Pit vipers, including rattlesnakes, copperheads and cottonmouths, account for most venomous snakebites in dogs across North America. Venom varies between species and can also differ among snakes of the same species with geography, age and season. A bite’s effects depend on factors such as the snake, venom dose, bite location and time to treatment.
Pit viper venom can injure tissue and blood vessels, trigger swelling and bleeding, disrupt clotting, damage muscle and contribute to low blood pressure or shock. Some rattlesnake populations, including Mojave rattlesnakes and certain timber rattlesnakes, can also cause clinically important neurologic effects. A dog with little visible swelling may still be seriously ill.
Dogs are often bitten on the face, neck or front legs. Swelling at those sites can look alarming, but airway compromise is uncommon, even after facial bites. A bite inside the mouth or behind the eye can pose greater concern. Noisy, stertorous breathing or elevated carbon dioxide in the blood can indicate respiratory compromise; oxygen or advanced airway support may be needed in rare cases.
Stabilization comes before snake identification
Owners should keep a bitten dog quiet and arrange immediate veterinary assessment. They shouldn’t handle or transport a dead snake, since a dead snake may still reflexively envenomate. A photograph taken from a safe distance may help with identification, but treatment decisions should focus first on the dog’s condition.
Tourniquets, tight bandages, cutting the wound, suction, ice and electric shock haven’t shown benefit and may worsen tissue injury. At the clinic, rapid assessment focuses on breathing, circulation, neurologic function, swelling progression, pain and signs of bleeding or hemolysis.
Tests and repeat checks help reveal changes
Initial evaluation commonly includes a blood count with platelet assessment, blood smear, serum chemistry, clotting tests and urinalysis. Blood gas analysis may help assess dogs with neurologic signs and possible reduced ventilation. Echinocytes—abnormally shaped red blood cells—can provide a useful clue in envenomation involving pit vipers and coral snakes.
Clinicians also watch for low platelet counts or fibrinogen, prolonged clotting times, red blood cell breakdown, muscle injury and acute kidney injury. Dark or unusually colored urine may reflect hemoglobin or myoglobin; both pigments can harm the kidneys. Because these problems can develop after the first examination, repeat assessments are an important part of care.

Antivenom and supportive care
Antivenom is the specific treatment for clinically significant envenomation. It can neutralize circulating venom and may limit worsening tissue injury, pain, clotting problems and cardiovascular instability. Early treatment matters: once venom has spread into tissues or irreversible injury has occurred, antivenom may be less effective. Progressive swelling, shock, clotting abnormalities, hemolysis, neurologic signs, severe pain or rapid deterioration commonly support its use. Copperhead bites may be less severe than rattlesnake bites, but decisions depend on the individual case.
Antivenom is generally given intravenously with close observation. True anaphylaxis is uncommon, though reactions can occur; the source article reports higher rates with whole IgG than with F(ab')2 products. Clinicians commonly begin the infusion slowly, with exceptions for intra-arteriolar bites or rapidly developing shock, and keep epinephrine available. Vomiting, hives, skin redness or low blood pressure warrant attention.
The number of vials depends more on the amount of venom than on a dog’s size. A small dog with a substantial venom exposure may need as many vials as a large dog. Routine antihistamine pretreatment remains controversial and is not recommended by the article’s authors.
Fluids help address low circulating volume caused by blood vessel leakage and fluid shifting into tissues. Severe cases may need substantial intravenous crystalloid support. Hetastarch is discouraged because it can interfere with platelet function. Blood products are rarely the main early treatment during the first 18 to 24 hours; antivenom and crystalloid fluids are the initial priorities. Fresh frozen plasma or whole blood may be considered for severe bleeding or clotting problems, though correcting venom-related abnormalities often depends on adequate antivenom. Opioids are preferred for pain; nonsteroidal anti-inflammatory drugs are generally avoided because of possible effects on platelets and kidney blood flow.
Coral snake bites bring neurologic risks
Coral snakes are elapids, and their venom is chiefly neurotoxic. Eastern coral snake envenomation can cause progressive weakness, paralysis, difficulty swallowing and reduced breathing. Hemolysis has been reported in about 40 percent of affected dogs. Severe illness may follow subtle local signs, and some dogs may initially appear well.
Respiratory failure can require mechanical ventilation and several days of intensive care. Coral snake antivenom remains standard where available, but it may have limited ability to reverse neuromuscular weakness once that weakness is established. These dogs need close respiratory monitoring and supportive care.
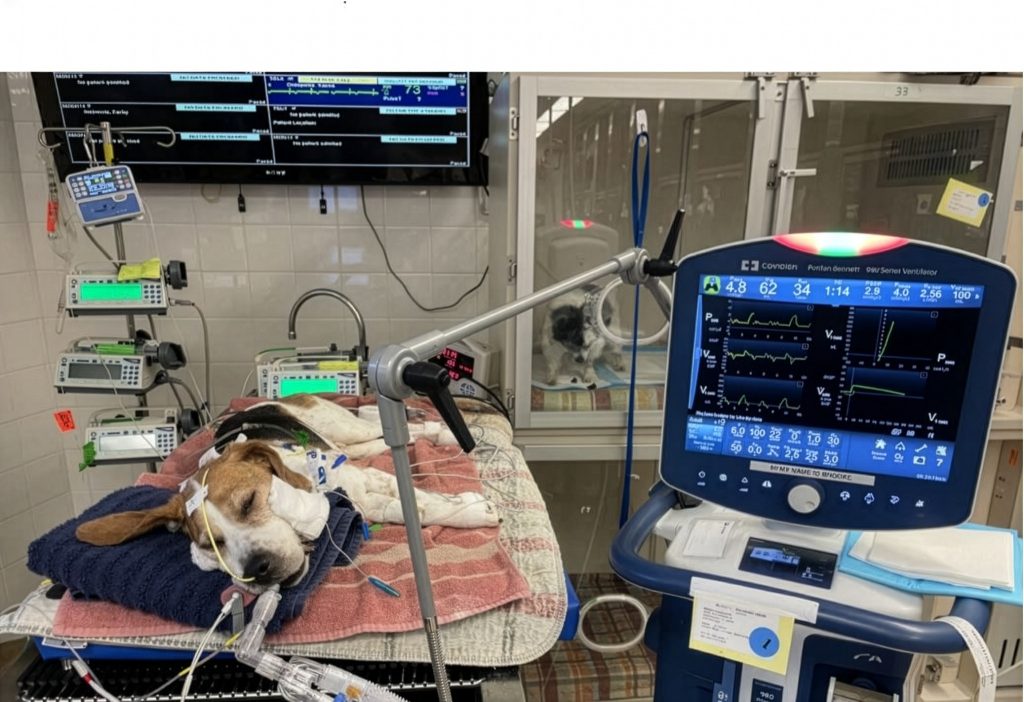
Research is testing an additional approach
Investigators are studying small-molecule inhibitors of secretory phospholipase A2, a toxin component in many snake venoms. An investigational inhibitor has shown preclinical activity against several species. The source article reports seven dogs treated for severe eastern coral snake envenomation with both antivenom and the inhibitor: four received it intravenously and three orally. All recovered despite marked neurologic weakness, without mechanical ventilation. Their hospital stays and care costs were substantially lower than those of historical comparison cases, and results from the first three dogs have been published.
These early cases are promising, but they don’t establish the inhibitor as standard care or show how much it adds to antivenom. Larger comparative studies are needed, including research in dogs with pit viper bites.

Individualize disputed treatments and prognosis
Routine corticosteroids aren’t generally recommended because evidence of benefit is lacking and there are concerns about wound healing and immune effects. They may be considered in selected circumstances, such as refractory shock or a type 3 hypersensitivity reaction. Preventive antibiotics are also debated: infection appears less common than once assumed, so decisions are typically based on wound appearance, tissue damage, contamination and the dog’s circumstances. The authors report that secondary infection in their pit viper cases is usually apparent by the third hospital day.
Prognosis depends on the snake, venom dose and bite location, how quickly care begins, antivenom access, and whether shock or respiratory failure develops. Age and other health conditions can also affect the outlook. Most dogs treated promptly for pit viper envenomation survive; delayed treatment, severe clotting problems and neurotoxicity are concerning features. Even extensive tissue death may heal with conservative care over 12 to 16 weeks, without surgery. Coral snake bites can carry greater risk because of respiratory paralysis, but intensive supportive care can still lead to recovery.
For owners, the clearest practical response is to limit the dog’s activity and seek veterinary care quickly after a suspected bite. For clinicians, early stabilization, timely antivenom when indicated and repeated checks for delayed complications remain the core of care as research continues.